Last Updated on August 19, 2026
Definition
- Mild hyperkalaemia: >5.5 – 6.0 mmol/L
- Moderate hyperkalaemia: >6.0 – 7.0 mmol/L
- Severe hyperkalaemia: >7 mmol/L
💡Tips
– Check formal RP result, to look for documentation of ‘haemolysed blood‘ in the formal report. If so, the ‘hyperkalaemia’ might not be reliable and RP should be repeated prior to giving treatment.
– Do ECG! If ECG shows features of hyperkalaemia, treatment should be given immediately instead of waiting for RP
Causes
Common causes: Can be ruled out easily from the formal RP result Abbreviation: DKA Notes: • Abdominal pain is a common presentation for DKA (with underlying newly diagnosed DM) Suspect tumour lysis syndrome especially if patient has haematological malignancy / recently done chemotherapy, and especially if patient also has other laboratory evidence of tumour lysis syndrome Most of the time these patients’ hyperkalaemia are chronic. However if ECG shows evidence of hyperkalaemia / patient symptomatic / severe hyperkalaemia, treatment would still be required prior to haemodialysis. Types of insulin 🚪 Prandial insulin (Bolus) 🚪 Basal insulin 🚪 Premixed insulin Source: CPG Management of Type 2 Diabetes Mellitus
• Pseudo-hyperkalaemia i.e.
Haemolysed blood
• Metabolic acidosis e.g.
DKA
• Medications e.g. potassium supplement (oral / IV), potassium sparing agent (e.g. spironolactone), ACE inhibitor
•
Tumour lysis syndrome
• Severe intravascular haemolysis e.g. severe malaria
• Tissue necrosis / crush injury
• Hypoaldosteronism e.g. Addison’s disease
•
End stage renal failure
Classification:
• Decreased renal excretion: Renal failure, Mineralocorticoid deficiency, Drugs, Acidosis
• Increased potassium intake
• Increase release from cells: shift out from cells (e.g.
insulin
• Short acting: Actrapid®, Humulin R, Insuman R, Insugen R
• Rapid analogue: Aspart (Novorapid®), Lispro (Humalog®), Glulisine (Apidra®)
• Intermediate-acting: Insulatard®, Hululin N, Insuman N, Insugen N
• Long-acting analogue: Glargine, Detemir, Degludec
• Mixtard 30, Humulin 30/30, Novomix 30, Humalog mix 25/75, Humalog mix 50/50
ECG Changes
• Loss of P waves • Broad QRS complex + tachycardia suggest ventricular tachycardia
• Tall tented T waves
•
Widened QRS complex
• Broad QRS complex without tachycardia suggests hyperkalaemia
• May indicate potassium more than 8 mmol/L!!! (absent P wave + broad QRS complex + absent ST segment)
• Prolonged PR segment
• ST elevation
Treatment
Oral medication – for mild hyperkalaemia
e.g. Oral Kalimate 5 – 10 g TDS // Oral Resonium A 5 – 30 g 4 – 6 hourly
Lytic cocktail – for acute treatment of hyperkalaemia
- IV Calcium gluconate 10% 10 mL over 10 minutes, then
- IV Dextrose 50% 50 mL, then
- IV Actrapid 10 units (0.1 mL)
💡Tips: Lytic Cocktail: Components of lytic cocktail: Tips: Clinical questions:
– HO should know how to prepare and administer
lytic cocktail
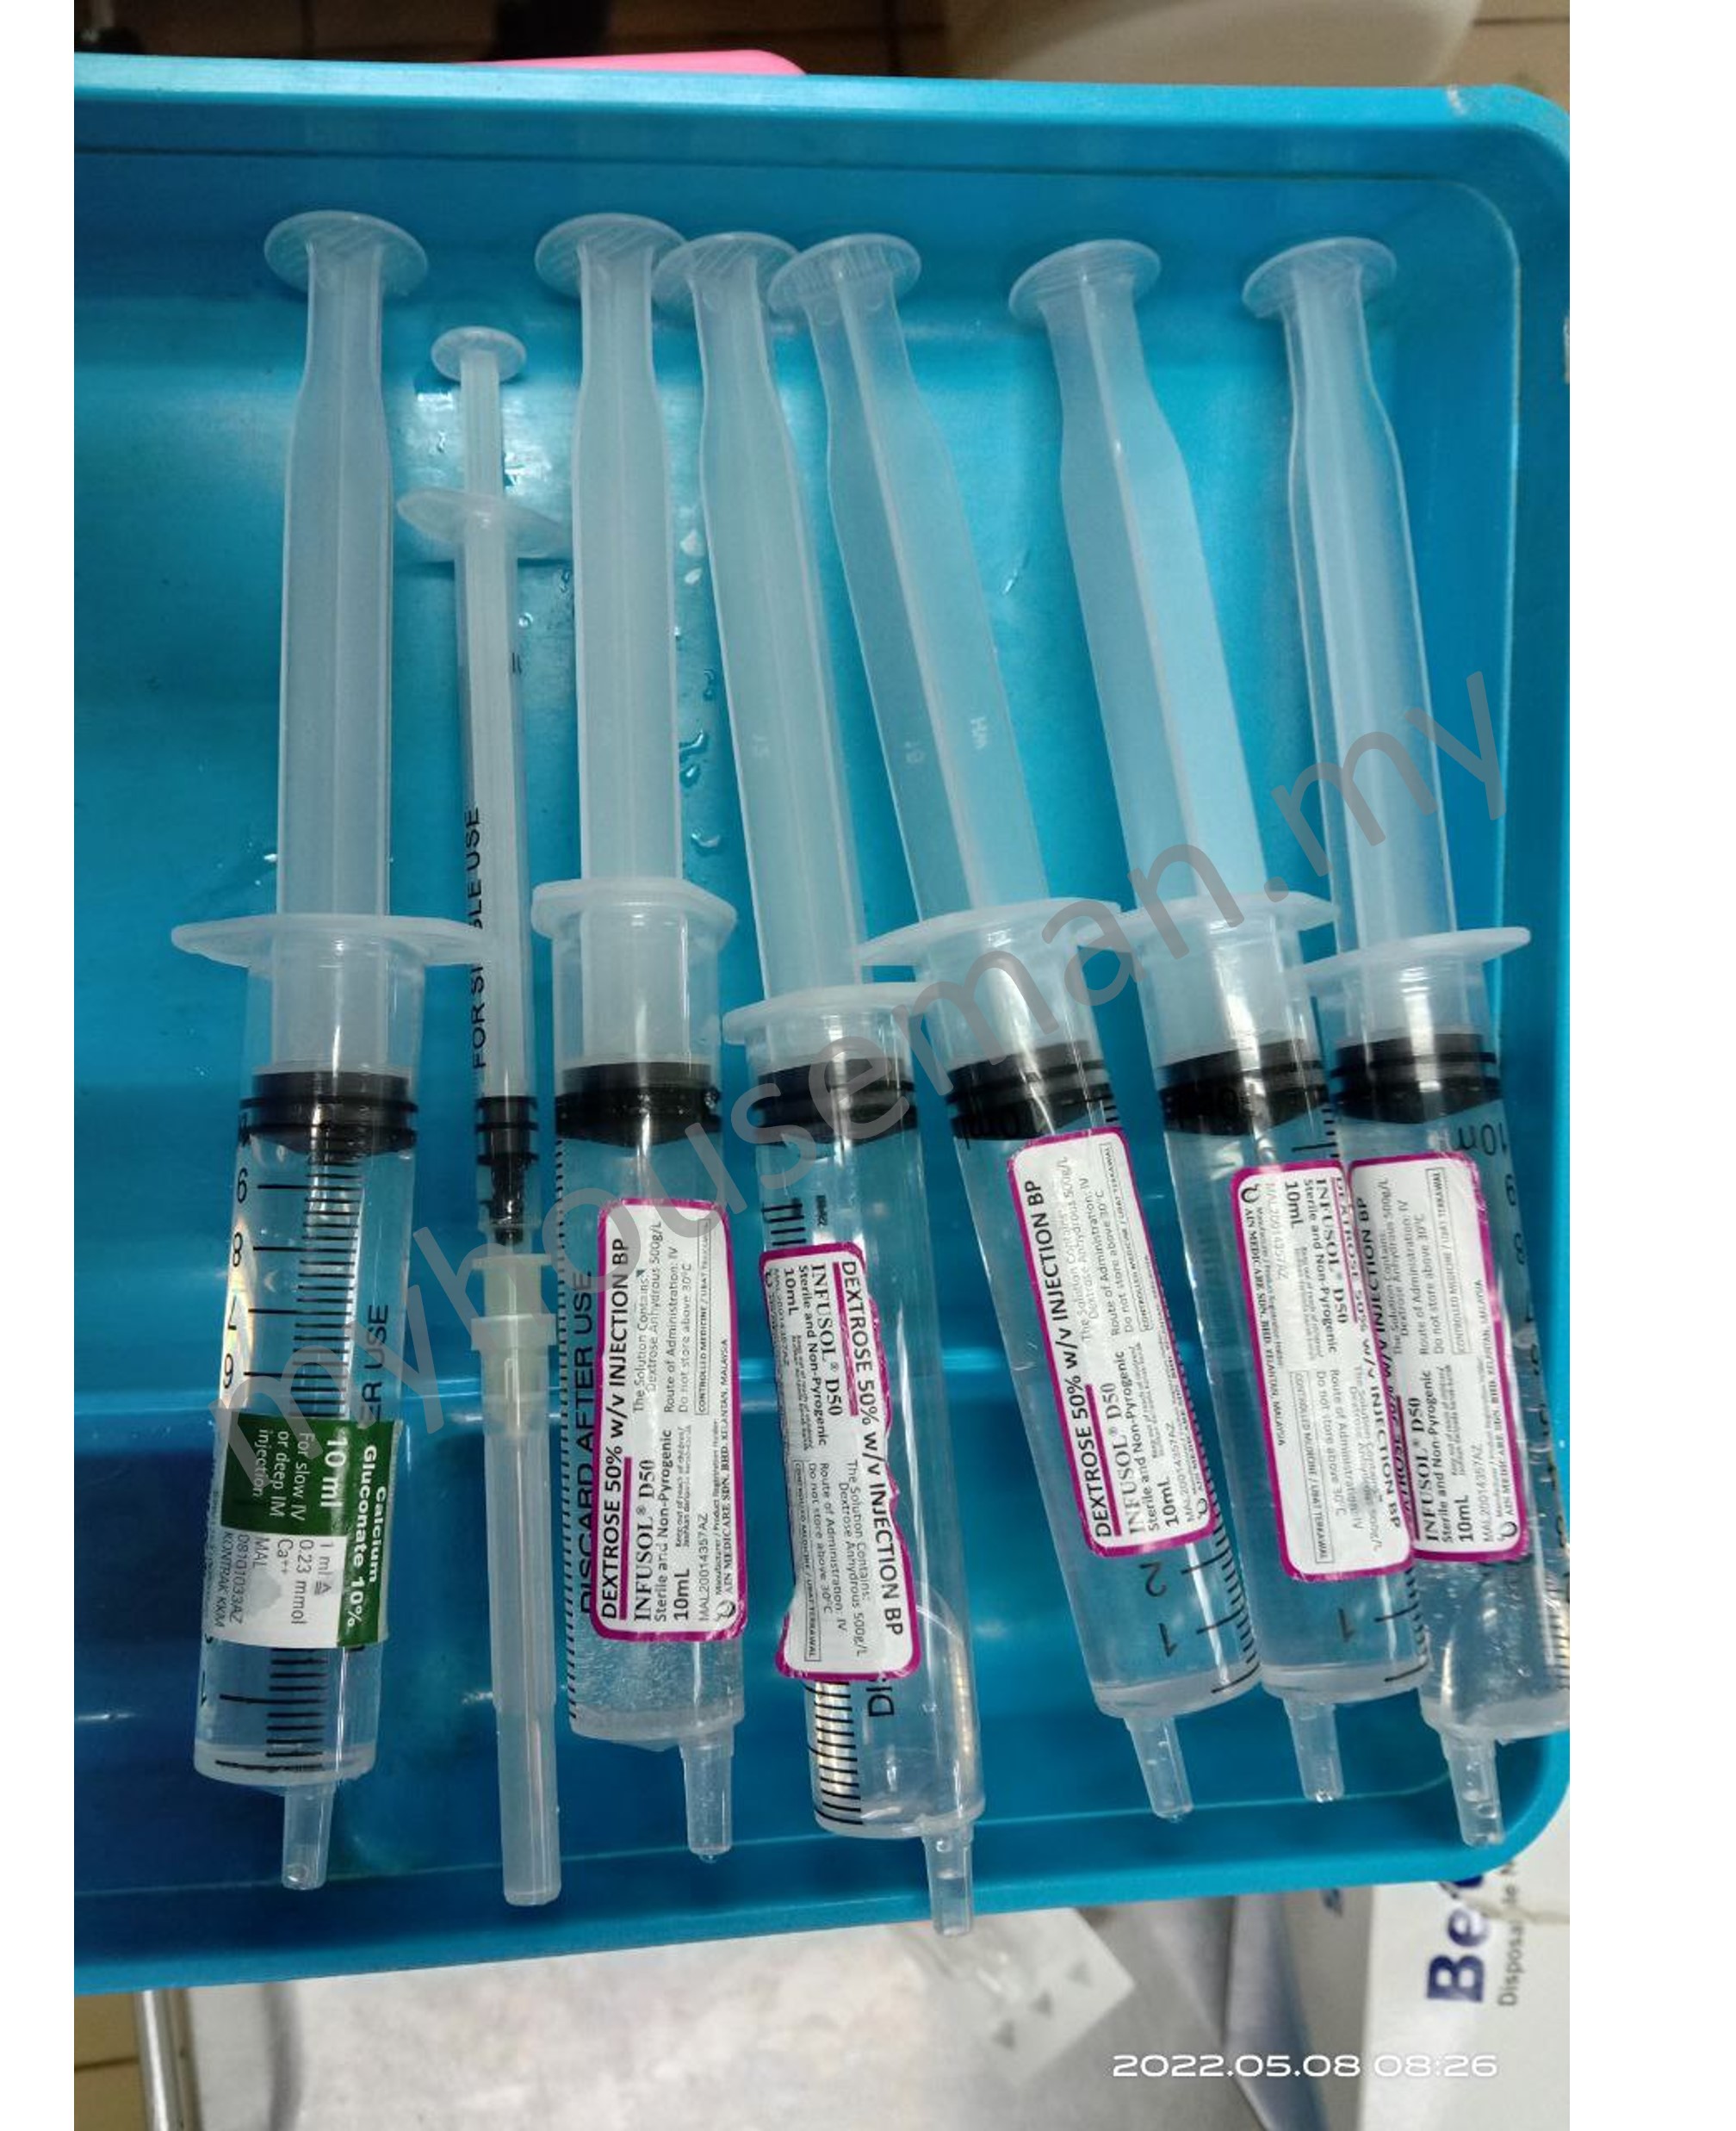
1. IV Calcium gluconate 10% 10 mL, give over 10 minutes, then
2. IV Dextrose 50% 50 mL, then
3. IV Actrapid 10 units (i.e. 0.1 mL)
1. Make sure patient is on cardiac monitor while serving lytic cocktail
2. IV Calcium gluconate 10% and IV Dextrose 50% look alike when they are in syringe. Therefore, you can use the sticker on the vial to stick on the syringe. Calcium gluconate must NOT be given as fast bolus!!!
3. Usually it's required to repeat renal profile (RP) after 1 hour to check if potassium level has been lowered
1. What is the mechanism of action of Calcium gluconate in hyperkalaemia?
Others
• Haemodialysis especially for ESRF patient whose HD is due / AKI
• Stop any potassium supplement (e.g. Mist KCl / Tab slow K / Potassium in IV drip)
Exam Tips
• ECG features of hyperkalaemia Lytic Cocktail: Components of lytic cocktail: Tips: Clinical questions:
• What are the components of
lytic cocktail
1. IV Calcium gluconate 10% 10 mL, give over 10 minutes, then
2. IV Dextrose 50% 50 mL, then
3. IV Actrapid 10 units (i.e. 0.1 mL)
1. Make sure patient is on cardiac monitor while serving lytic cocktail
2. IV Calcium gluconate 10% and IV Dextrose 50% look alike when they are in syringe. Therefore, you can use the sticker on the vial to stick on the syringe. Calcium gluconate must NOT be given as fast bolus!!!
3. Usually it's required to repeat renal profile (RP) after 1 hour to check if potassium level has been lowered
1. What is the mechanism of action of Calcium gluconate in hyperkalaemia?